


Today I'll talk about the red light therapy autism connection. I'll mostly follow conventional science here on this topic - I know many other fringe theories exist on this topic, but for convenience sake I'll stick to the scientific mainstream here.
Let's first talk about the basics of autism. After that, I'll consider light therapy for autism and other topics:
Autism Introduction
Autism is called "Autism Spectrum Disorder" (ASD) in the medical literature. It's complex disease originating in the nervous system that has been studied very extensively (1; 2; 3; 4; 5; 6; 7).
Not everyone is affected the same way by autism - that's why the word "spectrum" is included in its official medical name. Often, though, people with autism have a harder time learning, "Attention-Deficit Hyperactive Disorder" (ADHD), and a higher risk of epilepsy. Anxiety, depression, and sleep problems are also more frequently present.
Autism starts in childhood. There are often signs children are different than their peers and develop differently as well. The diagnosis is made according to the individual's development and observation by medical professionals. Worldwide, about 1% of children are affected but for some nations like the US that number exceeds 2%.
There's no cure for autism. Psychostimulants are often used in case ADHD is present but these often come with side effects. Otherwise, managing symptoms is extremely important for autism, as well as a focus on improving the quality of life. Usually, a team of practitioners is necessary to treat the person with ASD well. Timely interventions do generally enhance the quality of life.
Lately, light therapy for autism has also emerged a potential viable treatment. Today I'll zoom in on this topic:
Different Types Of Light Therapies For Autism
Many different light therapies for autism exist. Some have better scientific evidence going for them, and others worse.
But, to understand how light therapy works you'll have to look at the light spectrum. Different types of light exist. In physics, all types of light are part of the light spectrum (10; 11; 12).
There's invisible and there's visible light. The invisible light that the human naked eye cannot see, is made up of ultraviolet and infrared light. The visible light is made from all the colors of the rainbow, so violet, blue, green, yellow, orange and red.
All these different types of light have different effects on the human body. Some types of light don't just hit your tissues but enter your body - examples are UV light, red, and near-infrared light. When entering your tissues, the light has biological effects there.
Now, there are many types of light therapy for autism:
- Red light therapy for autism - which I'll break down into great detail soon.
- Infrared saunas for autism. Toxin exposure may play a major role in autism, for instance (13; 14; 15; 16; 17; 18). Although I'm not going to consider this topic in detail here, there's very strong evidence that infrared saunas can help you detox some types of toxins. Examples here are phthalates, BPA (a compound used in plastics), heavy metals, and others. Studies need to be executed on this topic though, to observe whether there's a link. And, infrared saunas for autism can also help because they counter depression and anxiety - a frequent symptom. Infrared saunas are akin to near-infrared light therapy autism.
- Sunlight has effects, in part through vitamin D (19; 20; 21; 22; 23). For upcoming mothers, vitamin D might reduce autism risk in early childhood. Vitamin D may also counter autism in childhood and low vitamin D may be a risk factor for developing autism. Please keep in mind here that I'm not advocating for vitamin D supplements here, unless it's very dark in your winter time. Time and time again, studies show far superior results with sunlight exposure over vitamin D supplements. Vitamin D may also counter hyperreactivity in autism.
- SAD lamps to set the circadian rhythm. Once more, sunlight is the way better option but but if there's no good sun available during your wintertime, SAD lamps may play a great role. Your body has a circadian rhythm, a 24-hour day and night cycle. Brightness during the morning tells your body it's daytime and darkness at night tells your body it's time to go to sleep. Morever, it turns out that circadian disruptions, so too much darkness during the day and too much bright light exposure at night, plays a major role in autism as well (24; 25; 26; 27; 28; 29). Get some red LEDs for sleep for a few hours before bedtime as an easy help to boost melatonin and improve the circadian rhythm. An SAD lamp is a light box therapy for autism, for instance.
- Tanning beds, although riskier and the medical mainstream doesn't consider tanning beds safe. Just know that there's a direct link between absence of sunlight exposure and autism risk (30; 31; 32; 33; 34). Tanning beds are a very imperfect replacement of the sun but if you have no other option, you may consider it in a safe way (never getting a sunburn). Again, natural light therapy autism is always best.
So all in all, there are many different light therapy & autism options. I'll consider red light therapy next, in more detail:
Red Light Therapy And Autism: The Latest Research
Summary: what the research says about treatment settings
Human studies have most often used near-infrared light around 810–850 nm on the forehead or scalp; newer case series use 1064 nm. Some protocols add a nasal applicator, while laser-acupuncture studies treat selected body and scalp points (39) (44) (52) (54).
Light exposure commonly lasts about 5–30 minutes, from twice weekly to daily, over four to eight weeks; some courses extend to several months (52) (53) (55). Both continuous and pulsed light have been studied, including 10- and 40-Hz protocols, but neither approach has been shown superior (44) (52) (53).
Reported surface doses sometimes approach 60 J/cm² per location, yet missing information often prevents reliable comparisons (39) (44). No wavelength, dose, treatment area or schedule has been established as best. These are studied protocols, not validated recommendations. Evidence remains preliminary and mixed; benefit beyond sham, lasting effects, who benefits and long-term safety remain uncertain (40) (41) (51).
Evidence checked through 16 October 2026.
Red light therapy is being investigated for communication, irritability, attention and other difficulties experienced by some autistic people. The term often includes invisible near-infrared light. Researchers have tested several approaches, including light applied to the scalp, inside the nose and at acupuncture points (44) (52) (54).
Some small controlled studies report benefits. However, improvement during treatment does not necessarily mean the light caused it. Expectations, ongoing therapies, attention from researchers and natural variation can also affect scores. This matters because two completed registry trials found substantially less separation between active treatment and sham than some earlier publications (41) (51) (55).
Reading the tables: Power in W or mW describes light output; irradiance in mW/cm² describes power per area; fluence in J/cm² describes energy per area. Doses below concern the treatment surface unless stated otherwise. Doses at different locations are not added together. Hz means pulses per second; duty cycle is the percentage of time the light is on.
Outcome measures: ASD means autism spectrum disorder; CARS is the Childhood Autism Rating Scale; SRS measures social responsiveness; AQ measures autistic traits; ABC measures challenging behaviors. A lower questionnaire score does not mean a diagnosis has disappeared. “Not reported” identifies missing source information; “could not verify” identifies details that accessible material did not allow us to confirm.
Human studies
The table combines published studies and clearly labeled trial-registry results, ordered by year. All involved diagnosed ASD, although some investigated additional outcomes such as urinary metals, gut bacteria or a co-occurring condition.
| Study population and design | Wavelength, dose and schedule | Device and application | Laser or LED | Results and limitations |
|---|---|---|---|---|
| 2026 — Guimarães et al. (37) One 6-year-old girl with diagnosed ASD, constipation, seizures and ADHD. Uncontrolled before–after microbiome case report. | 1064 nm, range 1050–1070 nm. 434 mW/emitter; 1.302 W per three-LED cluster. Reported skin irradiance ≈54 mW/cm²; estimated 32.4 J/cm² per 10-minute application. 10 minutes forehead + 10 minutes abdomen; 20 minutes/day for 90 days. Abdominal dwell distribution not reported; head and abdominal doses remain separate. | Handheld three-LED probe; manufacturer/model not reported. Right forehead, Fp2; lower abdomen/right lower quadrant. Active emission area 23.76 cm²; 7.5 mm from skin. | LED. Continuous/pulsed mode, frequency and duty cycle not reported. | Microbiome profile and caregiver-reported bowel/behavior measures changed from baseline; no control or post-course follow-up. Baseline sample was 93.14% unclassified, complicating interpretation. Stable medicines and ongoing behavioral care. Possible overlap with case 8 in Diaz et al.; independence could not verify (39). |
| 2026 — Zaharakis & Bogner (38) One 5-year-old boy with diagnosed ASD. Uncontrolled urinary-metals case report; clinical autism efficacy was not tested. | 660 nm. Nominal <5 mW peak total across six diodes; <1.5 mW time-average. Authors estimate 5–15 mW/cm² and 4.5–13.5 J/cm²/session. These are not verified per-site doses: calculation uses all 900 seconds despite scanning and ≤60 seconds/point. 15 minutes/session, three/day; 18 sessions over six days. | DCL-6R, Researched Elements Tech LLC. Six line beams; estimated illuminated area 0.1–0.3 cm². Frontal, temporal/parietal and occipital scanning described retrospectively; sites not prospectively logged. Nominal distance 1–2 cm; reported range 0–3 cm. | Laser, cycling through 9, 33 and 60 Hz, every two seconds. 30% duty cycle. Nominal peak and average output not independently measured. | Urinary aluminum increased; follow-up approximately two months. This does not establish reduced body burden or improved autism outcomes. No validated clinical outcome; incomplete safety capture; manufacturer-related conflict. Diet/supplements reportedly unchanged; other concurrent care inadequately documented. |
| 2026 — Diaz et al. (39) Eight people, ages 6–38, with diagnosed ASD. Prospective open-label case series. One twin initially received four weeks of sham before active treatment; no full-cohort sham comparison. | 1064 nm, range 1050–1070 nm. 1.59 W total aperture output; mean 100 mW/cm²; reported 60 J/cm² per forehead location/session. 10 minutes/location and total session; daily for eight active-treatment weeks; 56 scheduled active sessions. | CytonSys headset; model not reported. Right forehead, Fp2. Aperture diameter 4.5 cm; area 15.9 cm². Skin contact/distance not reported. | LED; continuous wave. No pulsing. | AQ scores fell in 7/8 from baseline. Attention testing included only three completers: sustained attention improved in one and impulse-control accuracy in two—exploratory, mixed findings. Varied medicines, supplements and therapies continued; two participants reported transient nightmares. No post-course follow-up. Possible overlap with the microbiome case above. |
| 2026 registry results — NCT06352372 (40) Six children with diagnosed ASD plus epilepsy and/or epileptiform EEG; open-label. Five assessed at week 11, four at week 15. Registry results, not a journal efficacy report. | 850 nm in linked protocol. Power, mW/cm² and J/cm² not reported. Titration 2→10 minutes/session, twice/week for ten weeks, 20 sessions; protocol then lists eight taper sessions through week 14. Registry emphasizes the ten-week phase; actual delivered totals could not verify. | Cognilum, JelikaLite; protocol describes ten LED circuit boards in headgear. Scalp application with glycerin. Exact site map, illuminated area and optical contact/distance not reported. | LED; 40 Hz. Duty cycle and peak/average output not reported. | Mean CARS: 37.7 baseline, n=6; 34.2 week 11, n=5; 37.4 week 15, n=4. Changing samples prevent a simple paired-change interpretation; no control. Usual therapies required stable. One seizure recorded; causality not established. Too small to establish seizure safety or lasting benefit; no clearly untreated follow-up. |
| 2026 registry results — NCT05363982 (41) Adults with diagnosed ASD; double-blind randomized sham trial. 41 consented; 30 randomized, 15/arm; 25 exposed; 21 completed. SRS analysis: 13 active/12 sham. | 850 nm. Output power, mW/cm² and J/cm² not reported in accessible registry/protocol. Daily for eight weeks; 56 scheduled sessions. Titration 20→30→40→50 minutes, as tolerated. Both sides simultaneously, so site and total session durations match. | Niraxx G1 headband, Niraxx. Bilateral forehead, centered across frontal EEG sites. LED area and precise skin contact/distance not reported. | LED. Continuous/pulsed mode, frequency and duty cycle not reported in accessible protocol. | Mean SRS change: −25.7 active versus −25.3 sham. No clear average advantage in posted means; no inferential comparison reported. Response counts of 4/13 versus 2/12 are not proof of superiority. Stable medicines allowed. Headache: 7/15 active versus 2/15 sham. Attrition, small sample; eight-week results only. |
| 2025 — Fradkin et al. (42) Children ages 2–7 with diagnosed ASD; open-label, no concurrent control. 25 enrolled; 22 completers in results, but abstract says 23. | 850 nm; 150 mW maximum per LED, six LEDs. Average/on-pulse basis unspecified; irradiance and J/cm² not reported. Titration 2→12 minutes/session; per-site timing not reported. Twice/week for eight weeks. Text also places two-week titration before that course; total sessions not consistently specified. | JelikaLite investigational headwear, described as the device used previously. Six emitters targeting frontal, language, occipital and default-mode-network regions. Illuminated area and skin contact/distance not reported. | LED; 40 Hz. Duty cycle not reported. | CARS fell approximately 36.5→29.7 from baseline. EEG associations in 15 children were exploratory. Four headaches; 17 children had parent-reported hyperactivity at least once. Behavioral therapies allowed; regular medicines excluded. No post-course follow-up. Historical sham data reproduced in the paper are not a new control group. |
| 2024 — Pallanti & Muretti (43) One 24-year-old man with SCN2A-related diagnosed ASD. Uncontrolled case report. | 810 nm. Reported output per emitter: posterior 100 mW, anterior 75 mW, nasal 25 mW. Corresponding densities 100/75/25 mW/cm²; doses 60/45/15 J/cm² per location. Five sessions/week; 60 sessions. Course conflict: endpoint labeled two months, incompatible with that schedule. Session duration not reported. | Vielight Neuro Gamma; four scalp clusters plus left-nostril applicator. Targets default-mode-network regions. Beam area and skin contact/distance not reported. | LED; 40 Hz. Duty cycle and average/on-pulse basis not reported; stated doses cannot be independently verified. | Rigidity, repetitive behavior and disability ratings improved from baseline; reported persistence at 12 months. Stable atomoxetine and lorazepam continued. Single case without blinding/control; no adverse effects reported. Does not establish efficacy for SCN2A-related ASD generally. |
| 2024 — Fradkin et al. (44) Diagnosed ASD, ages 2–6. Randomized sham-controlled trial: 34 recruited; 30 completed—16 active, 14 sham. | 850 nm; six-LED device maximum total output <300 mW, elsewhere rounded to 300 mW. Average/on-pulse basis, mW/cm² and J/cm² not reported. Titrated to six minutes of light/session at simultaneous scalp sites; twice/week, eight weeks, 16 scheduled sessions. Approximately 30-minute appointments also included EEG. | Cognilum, JelikaLite; manufactured by Sterling Medical Devices. Scalp sites targeting default-mode and language networks. Illuminated area and skin contact/distance not reported. | LED; 40 Hz. Duty cycle not reported. | CARS improvement exceeded sham by 7.23 points, 95% confidence interval 2.36–12.11. Exploratory EEG group-by-time result did not reach significance. Many continued behavioral, speech or occupational care; regular medicines and seizure history excluded. Small trial; one allocation error analyzed by treatment received; developer involvement. No post-course follow-up. |
| 2023 — Elsheikh et al. (45) 30 children with diagnosed ASD, randomized 15 laser acupuncture/15 no laser. Another 15 neurotypical children supplied biomarker comparisons, not an autism-treatment control. | 850 nm; 200 mW treatment applicator, reported in the publisher’s indexed methods. Twice/week; 12 sessions over six weeks. Irradiance, verified J/cm², exposure per point and total session duration could not verify from accessible primary material. | Laser acupuncture. Manufacturer/model, exact point map, beam area and contact/distance could not verify. | Gallium-aluminum-arsenide laser. Continuous/pulsed mode, frequency and duty cycle could not verify. | Severity and language measures improved more than the no-laser group. Blood BDNF decreased in the laser group; miR-320 did not change. Small trial without sham; biomarker change does not establish clinical mechanism. Concurrent-care details, adverse-event methods and post-course follow-up could not verify. |
| 2023 registry results — NCT04895605 (51) 40 children, ages 5–12, with diagnosed ASD and irritability. Masked randomized trial: 19 active/21 placebo. Separate 2020–2022 cohort from Leisman 2018. | 640 ±10 nm; 7.5 ±1 mW per diode, two diodes. Peak/average basis unclear. Protocol reports 2.10 J total/session; calculation basis not reported. Irradiance and J/cm² not reported. Five minutes total scanning/session; site dwell not reported. Twice/week; eight sessions/four weeks. | Erchonia HLS; two line-beam diodes. Swept between temporal regions across back of head; four inches, approximately 10.2 cm, above skin. Illuminated area not reported. | Laser; variable-frequency pulsing; specific frequency not reported. 50% duty cycle. Continuous scanning does not mean continuous-wave emission. | ABC irritability fell 8.68 active versus 6.05 placebo at four weeks. Calculated difference: 8.68 − 6.05 = 2.63 points, below the registry’s 8.5-point success threshold; no inferential result posted. Stable existing care. Four-week post-course follow-up planned; primary posted result is treatment endpoint. No adverse events posted; manufacturer-sponsored. |
| 2022 — Pallanti et al. (52) 21 children, ages 5–15, with diagnosed ASD. Retrospective, uncontrolled study. | 810 nm. Reported posterior/anterior/nasal output 100/75/25 mW per emitter; densities 100/75/25 mW/cm²; doses 60/45/15 J/cm² per location/session. 20 minutes/site and total/session, twice/day, five days/week for six months. Total sessions not reported. | Vielight Neuro Alpha and Gamma. Four scalp clusters: Fpz, Cz, T3, T4; nasal applicator. Approximately 1 cm²/emitter. Headset and nostril clip; precise optical contact/distance not reported. | LED; morning 10 Hz, evening 40 Hz. Duty cycle and peak/average basis not reported. Doses cannot be independently reconciled with exposure duration without this information. | Autism, attention, sleep and family-stress ratings improved from baseline at three/six months; assessments occurred during treatment. Stable behavioral/pharmacological care plus activities during sessions. Retrospective parent-administered treatment; no control. Claimed deep penetration was not a measured brain dose in these children. |
| 2022 — Ceranoglu et al. (53) 11 eligible adults with diagnosed ASD; 10 treated/completed, ages 19–55. Open-label, no sham; nine also had ADHD. | 830 nm; almost 1 W/LED cluster, two clusters ≈2 W total. 33.2 mW/cm²; reported maximum 60 J/cm² per forehead site/session. 20→25→30 minutes, both sites simultaneously; twice/week, eight weeks; 16 scheduled sessions. Power conflict: discussion instead states 655 mW/device. | Photomedex Omnilux New U; two cluster heads. Left/right forehead, F3/F4; 28.7 cm²/head, 57.4 cm² combined. Exact contact/distance not reported. | LED; continuous wave. 100% duty cycle reported. | SRS scores improved from baseline; 5/10 met the prespecified response definition. No controlled efficacy estimate. All continued psychotropic medicines; psychotherapy allowed. Three transient events: headache, insomnia or warmth. No post-course follow-up. ADHD findings concern a co-occurring condition, not an independent autism trial. |
| 2020 — Surapaty et al. (54) 46 children, ages 2–6, with diagnosed ASD. Double-blind randomized trial: 23 active/23 inactive-probe sham. | 785 nm; 40 mW single probe, device maximum 50 mW. Reported 1 J/point, not 1 J/cm². Irradiance/fluence not reported. Per-point duration: 50 seconds calculated from authors’ rule: 2 × (1 J ÷ 0.040 W), assuming their stated doubling for modulated operation. Total session time not reported. Three/week; 18 sessions, six weeks. | RJ-Laser Laserpen Praxis, type 130. GV20, HT7, LI4, SP6, ST36, GB34, LR3 and scalp speech area. Beam area and exact optical contact/distance not reported. | Laser; Nogier G modulation, 18,688 Hz. Duty cycle and average/on-pulse power basis not explicitly reported. | Speech comprehension, expression and social interaction improved more than sham; parent sensory-report outcome did not differ between groups. Both groups received sensory-integration occupational therapy. Follow-up ended with treatment; informal parent safety reporting. No adverse events reported. |
| 2018 — Leisman et al. (55) 40 children/adolescents, ages 5–17, with diagnosed ASD and irritability. Randomized 21 active/19 placebo. Follow-up papers concern the same cohort. | 635 nm; reported output 15 mW. Whole-device versus emitter scope and average/peak basis not specified. Five minutes total/session; site dwell times not reported. Twice/week; eight sessions, four weeks. mW/cm² and J/cm² not reported. | Erchonia EAL Laser, as named in the original chapter. Base of skull and temporal regions. Beam area and contact/distance not reported. | Active: pulsed laser; frequency/duty cycle not reported. Placebo: red 635-nm LED; full sham dosimetry not reported. | Adjusted ABC irritability improvement 15.17 points greater than placebo. Original assessments extend to week eight; later reports extend to 12 months, with placebo crossover complicating long-term comparisons. Stable medicines/therapies continued. Manufacturer funded; small single-center trial. Later age analyses are exploratory, not independent trials. |
Later long-term and crossover reports from the Leisman research program follow the original cohort and should not be counted as new randomized trials (55) (60). The 2024 paper discussing autistic traits alongside ADHD is a review, not a new treatment experiment (62). Registrations without posted results, such as NCT06006637 in the record checked here, describe research plans rather than demonstrated benefits (63).
Animal and laboratory studies
The studies below include animal models and laboratory measurements of animal tissue. The healthy-rat safety study provides indirect evidence, while the valproate experiments model selected autism-like features. Two acupuncture experiments used blue light, so their findings should not be presented as evidence for a red-light protocol (56) (57) (58) (59).
| Study population and design | Wavelength, dose and schedule | Device and application | Laser or LED | Results and limitations |
|---|---|---|---|---|
| 2025 — Gutiérrez-Menéndez et al. (56) 42 healthy male juvenile rats, across two experiments. Light versus sham, with cage controls for glial analysis. Indirect developmental-safety study; no autism model. | 810 nm; reported 40 mW beam output; irradiance 65.6 W/m² = 6.56 mW/cm², unit conversion; and 46.5 J/cm²/day. These values conflict with the stated beam area and exposure; no definitive corrected dose calculated. 36 cycles/session: 40 seconds on/10 seconds off; 24 minutes light within 30 minutes. Five daily sessions, postnatal days 24–28. | Laser manufacturer/model not reported in this paper. Shaved frontal scalp; beam area 0.0495 cm². Exact contact/distance not reported. | Continuous-wave laser during each on-period, with interrupted treatment. Calculated cycle rate: 1/50 seconds = 0.02 Hz. Calculated duty cycle: 40/50 × 100 = 80%, assuming repeated cycles without extra pauses. | No detected glial/cytokine differences at postnatal day 29. Short-term, selected laboratory endpoints; not proof of long-term child safety. Reported 0.8% brain transmission derives from earlier rat-skull measurements outside the body, not dosimetry in these living animals. No therapeutic co-treatment. |
| 2022 — Kim, Hong & Ahn (57) Prenatal valproate mouse model; four groups: vehicle, light only, valproate, valproate + light. 48 pups at day ten, distributed 14/15/8/11; number of dams not reported. | 830 nm; 70 mW/cm²; reported 42 J/cm² per maternal abdominal application. Total beam power not reported. 10 minutes/location and total/session; three prenatal sessions, approximately every other day. Exact gestational treatment dates could not verify. | Laser manufacturer/model not reported. Maternal abdomen; noncontact, five-centimeter distance. Source labels spot size “Diameter = 7.07 cm²”: conflicting dimension/unit, not silently corrected. | Laser; continuous wave. No pulsing. | Selected offspring social, cognitive and inflammatory outcomes improved versus valproate controls. Behavior assessed through postnatal day 54; tissue at day 56. Behavioral analyses excluded females because they lacked behavioral changes. Uncertain litter-level independence; no measured fetal-brain dose. Does not test treatment of autistic children or establish pregnancy safety. |
| 2017 — Khongrum & Wattanathorn (58) 24 male rat pups; valproate model. Four groups of six: untreated control, valproate alone, valproate + off-point laser, valproate + HT7 laser. | 405 nm: blue light, not red/near-infrared. Reported 100 mW laser output; mW/cm² and J/cm² not reported. 10 minutes treatment/day; allocation between bilateral points unclear. Daily on postnatal days 14–40; 27 scheduled sessions. | Xinland International; model not reported. Bilateral HT7 wrist points; beam diameter 500 µm. Contact/distance not reported. | Laser; continuous wave. No pulsing. | Selected cerebellar oxidative-stress, inflammatory and GABA-related markers improved versus valproate controls; terminal assessment around day 40. Mechanistic animal evidence, not a human clinical outcome. Valproate induced the model; it was not an accompanying autism treatment. |
| 2015 — Khongrum & Wattanathorn (59) 40 rat pups, four groups of ten, with five males/five females per group. Valproate model with untreated, valproate-only and off-point laser comparisons. | 405 nm blue light; reported 100 mW laser output. Irradiance/J/cm² not reported. 10 minutes treatment/day; per-point allocation unclear. Daily on postnatal days 14–40; 27 scheduled sessions. No definitive dose calculated. | Xinland International; model not reported. Bilateral HT7 wrist points; beam diameter 500 µm. Contact/distance not reported. | Laser; continuous wave. No pulsing. | Selected social, motor, memory and oxidative-stress outcomes improved versus model controls; some antioxidant enzymes did not change. Terminal sampling after the course. Small animal study using blue light. Valproate timing conflicts between methods and discussion: postnatal day 14 versus nine. |
Other laboratory work is still more indirect. For example, a rat fear-learning study examined how light affected brain metabolism and retention of fear-extinction memories—the ability to remember that a previously threatening cue is now safe. It did not study autism or an autism animal model (61).
What does the overall evidence mean?
Red light therapy remains an experimental approach for autism. The positive findings justify further investigation, but the contrast between encouraging uncontrolled reports and less convincing sham-controlled registry results makes it premature to recommend a particular device or protocol (39) (41) (51) (53).
The most useful next studies would measure outcomes important to autistic people and families, report complete device settings, and follow participants after treatment stops. For now, the published protocols should be understood as research methods rather than validated home-treatment instructions or a reason to replace individualized educational, communication, behavioral or medical support (40) (44) (56).
Light Therapy And Sound Therapy In Combination
What about combining light and sound therapy for autism? Sound therapy seems to have positive effects on autism in some studies (46; 47; 48; 49; 50). Other studies disagree and claim sound therapy has no effect. But, that conclusion is made because there's insufficient evidence according to some reviewers of all available studies.
Because some studies do show positive effects of sound therapy for autism, I think there's little harm in trying it. The only downside here is opportunity cost, once you opt for a less well-validated therapy, you've got less time to spend on better validated therapies.
Light Therapy As A Potential Treatment For Autism
Light therapy certainly has great treatment potential for autism. For the best results, you'll probably have to combine several options at the same time.
For instance:
- Use red light therapy once daily, but start very slow with a lower dose.
- Ideally, get sunlight exposure in the morning and in the afternoon. The morning exposure is perfect for setting the circadian rhythm. The afternoon exposure is great for building vitamin D, inflammation, blood flow, and many other factors.
- At night, use Red LEDs For A Few Hours Before Bedtime or get some Swanwick blue-light blocking glasses (code FERGUS saves) for the night. You can get kids glasses too at Swanwick. These blue-light blocking glasses prevent blue and green light from entering the eye and help your body increase its melatonin levels.
So what are the best products for autism? For brain-only devices, I'd check out the following articles:
 Alex Contributor Account

The Neuronic Neuradiant 1070 is a helmet specifically made for brain treatment. Alex makes a preliminary review of this product in this video.
Also, you may want to check out the video Alex created on the Vielight - which I discussed earlier in relation to red light therapy for autism:
Discount code ALEX10 saves you on the Vielight. You may also want to check out Alex Fergus' interview with Dr Lew Lim:
 Alex Fergus
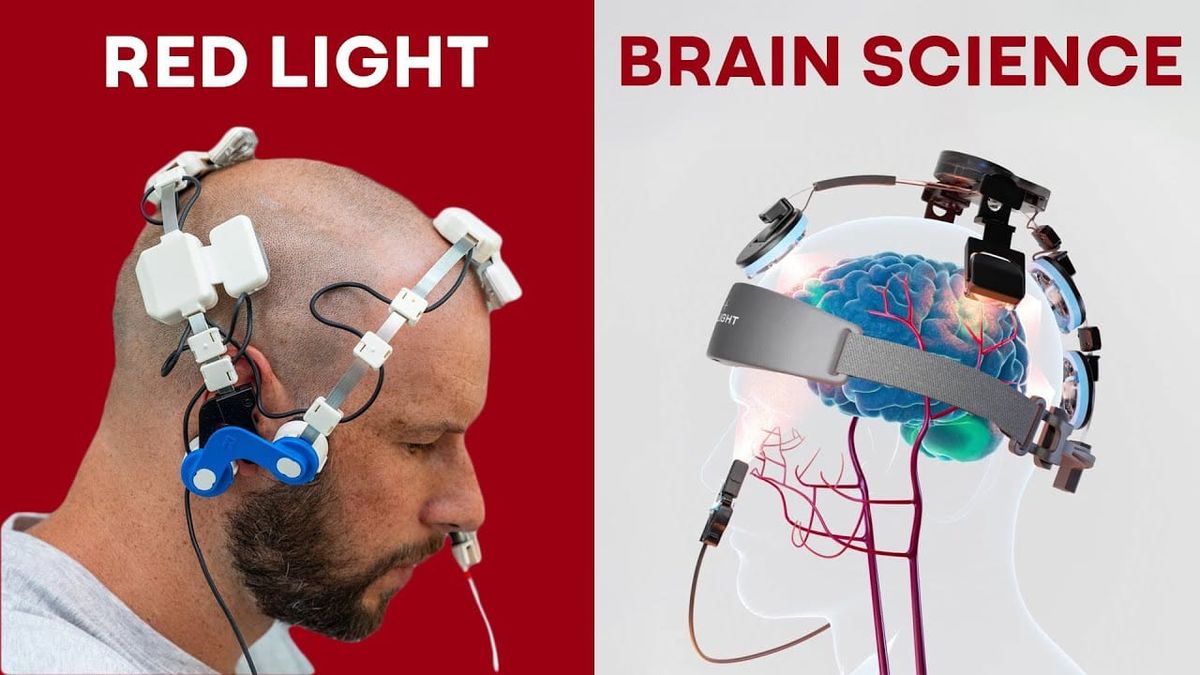
In this video, Alex Fergus interviews Vielight founder and CEO Dr Lew Lim about his products for the brain, and upcoming products.
Also, I recommend watching the following video, for a red light therapy panel - that panel can treat both the brain and the gut:
 Alex Fergus

In this article listed above, Alex compares the best red light therapy panels on the market.
Current Treatment Options For Autism
Current treatment for Autism is extremely broad. This ranges from special education to help with self-care, meditation, support on the job market later on, and so forth. Treatment options are extremely complex because so many children are affected. And, early treatment generally helps well into adulthood, which is why a lot is invested in this area.
Red light therapy for autism can work and generally has few side effects. I do recommend getting the aid of a clinician for treatment, as applying red light therapy to the brain is not 100% side effect-free if there's a condition present. You should be able to use red light therapy for autism together with any other autism treatments, however. And, many of these treatments including educational, occupational, mediation, pharmacological, and so forth, should even work well together with red light therapy.
Again, treatment options for autism is an extremely complex topic that I can't fully cover here in a few sentences.
Evidence, Testimonials & Real Life Cases
Yes, you can find many cases online where light therapy for autism works. I'll just zoom in on one case here, which is a mother who uses a light therapy box for autism during the winter months. Here's what she writes about her experience using a light box for autism:
"Since phototherapy requires time and consistency, you should set the light box on a table or desk. In this way, your child can read, use a computer, study, watch TV, or eat while having phototherapy. But parents should stick to a therapeutic schedule – and never overdo it.
Phototherapy doesn’t cure SAD, depression or other conditions, but it often eases symptoms, increases energy levels, and helps the child feel better about himself/herself – and life. Phototherapy can start to improve symptoms within just a few days. In some cases, though, it can take two or more weeks.
Phototherapy isn't effective for every child on the autism spectrum, but parents can take steps to get the most out of it and help make it a success" (51).
I recommend doing some searching on forums and you'll find that many parents have had success with light therapy. Also, keep in mind that the SAD light box is probably not your best option, but great if it's a very dark winter!
Conclusion: The Future Of Light Therapy And Autism
Light therapy for autism seems extremely promising, although more research is needed. Preliminary studies show good benefits that can be life-changing over time. For the best results, it's smart to combine sunlight, red light therapy, and blocking blue light at nighttime.
Frequently Asked Questions:
Below I'll answer a few frequently asked questions:
Can Red Light Therapy Help People With Autism?
Depending on your philosophy on medical research, the answer is "yes" or "no". Some people don't believe that there's evidence unless there are many peer-reviewed high-quality human studies available - in that case, your answer is likely "no".
If you think the promising preliminary studies already yield some evidence, then the answer is "yes". I fall in the latter category and think we can't always wait until (expensive) perfection before drawing conclusions and starting to do some testing.
Why Is Light Therapy Beneficial For Autism?
Many biological effects exist why light therapy is beneficial for autism, such as increased blood flow and vitamin D, better energy production, greater relaxation, enhancement of well-being and counteracting anxiety, and so forth.
Is It Safe to Use Light Therapy For Autism?
I recommend checking out the interview with Dr Randy Beck on red light therapy safety for brain disorders:
Dr Randy Beck makes a compelling case you'll have to be careful with red light therapy for the brain, with brain disorders.
So, to err on the safe side of the equation, let a clinician help you integrate light therapy into the life of a person with autism.
Items Mentioned
- Red LEDs For A Few Hours Before Bedtime
- Vielight Products - code ALEX10 saves
- Neuronic Neuradiant 1070 Helmet - code ALEXF5 saves
- Red Light Therapy Panel Comparison - with wall panels to target big areas of the body
- Cera Thrive - for combined brain-gut treatment. No discount available
This is a post by Bart Wolbers of Lighttherapyinsiders. Bart finished degrees in Physical Therapy (B), Philosophy (BA and MA), Philosophy of Science and Technology (MS - with distinction), and Clinical Health Science (MS), has had training in functional medicine, and is currently chief science writer.







